Scientific article · Sources checked 2026-10-21
Tretinoin Strength and Skin Irritation: What a 48-Week Comparison Actually Measured
Two tretinoin creams produced similar observed photoaging improvement despite different irritation levels. The result is informative—but it belongs to specific study preparations, clinical assessments, and tissue measurements.
Public-source editorial review. No clinician sign-off, firsthand test, personal prescription assessment or supplied-package inspection claimed.
A higher percentage on a tretinoin cream does not, by itself, establish a larger visible benefit. In a 1995 double-blind comparison, 0.1% and 0.025% topical tretinoin creams both improved facial photoaging relative to vehicle over 48 weeks. The higher concentration caused significantly more redness and scaling, while the investigators found no clinically or statistically significant efficacy difference between the active creams. That separation makes the study useful for examining the relationship between concentration, irritation, and improvement.
It also requires careful reading. The 99 people described in the indexed abstract were study completers, not a documented original enrollment total. Tissue changes were not percentages of wrinkle reduction, and a finding of no significant difference was not proof that the creams were equivalent. This analysis uses the indexed primary report abstracts and available official RENOVA labeling, rather than a review of all full articles, protocols, or supplements. The central question is how far each finding travels beyond the preparation actually studied.
Read through the preparation
Study facts at a glance
Study population: Ninety-nine patients with photoaging completed 48 weeks: 32 using 0.1% tretinoin, 35 using 0.025%, and 32 using vehicle. Source 1
Clinical comparison: Both active creams improved facial photoaging compared with vehicle; no clinically or statistically significant efficacy difference was reported between concentrations. Source 1
Tolerability: Redness and scaling were statistically significantly greater with 0.1% than with 0.025% tretinoin; the abstract does not provide event rates. Source 1
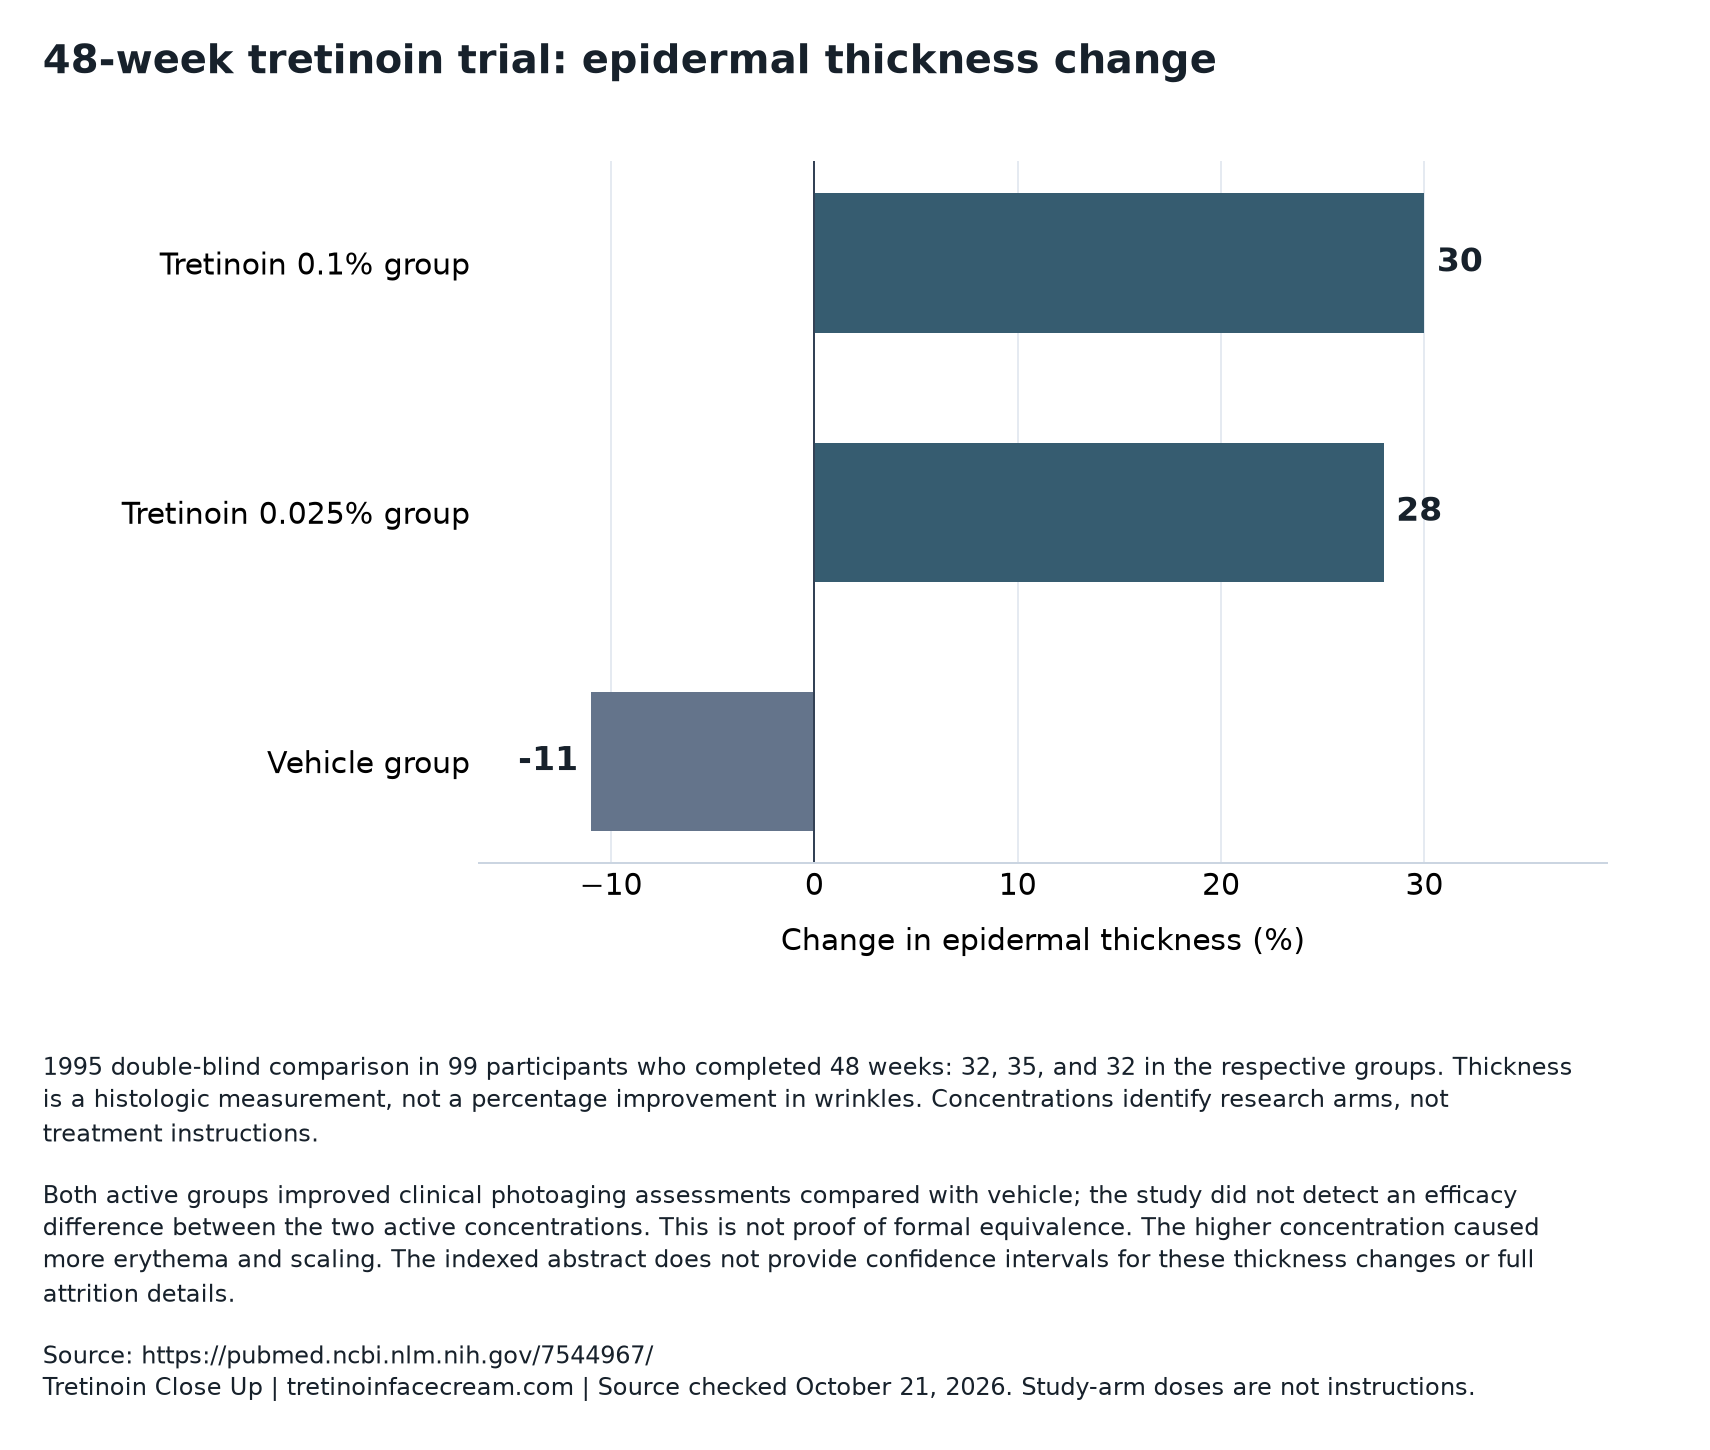
Tissue findings: Epidermal thickness increased 30% and 28% in the active groups, while vascularity increased 100% and 89%. These are not cosmetic response percentages. Source 1
Product-specific labeling: RENOVA 0.02% has a limited indication for mitigating fine facial wrinkles alongside comprehensive skin care and sunlight avoidance—not universal approval to reverse skin aging. Source 3
The comparison involved three creams and 48 weeks
The 1995 study compared topical tretinoin, also called all-trans-retinoic acid, at two concentrations with vehicle cream. Vehicle means the cream preparation without the active drug; it is a more informative comparator than no treatment because a cream base can itself affect skin condition and appearance. Participants used their assigned cream once daily for 48 weeks. These are historical study exposures, not instructions for an individual regimen.
The report describes a double-blind comparison, meaning treatment identity was concealed from participants and assessors. Its indexed abstract does not explain the allocation procedure or establish the number originally assigned to treatment. It reports 99 completers: 32 in the 0.1% group, 35 in the 0.025% group, and 32 in the vehicle group.
Clinical assessment concerned facial photoaging—skin changes associated with chronic sunlight exposure. Investigators also examined skin tissue before and after treatment, including thickness, vascularity, and immune markers. The abstract does not identify a prespecified primary endpoint or provide the clinical rating scale, baseline severity distribution, or detailed eligibility criteria. Those omissions limit reconstruction of the trial, even though its central comparison is clear.
Read the underlying chart data: download CSV or download the source-labeled chart.
Similar observed benefit is not demonstrated equivalence
Both tretinoin concentrations produced statistically significant overall improvement in facial photoaging compared with vehicle. Between the two active creams, the investigators reported neither a clinically significant nor a statistically significant efficacy difference. This supports a straightforward conclusion: within this study, the stronger cream did not demonstrate a larger clinical benefit.
It does not establish formal equivalence or noninferiority. Such designs require a defined margin specifying how much difference would still count as acceptably similar, together with an analysis precise enough to test that margin. The abstract supplies neither an equivalence framework nor confidence intervals for the active-treatment difference. A small study can fail to detect a real difference, particularly if clinical scores vary substantially.
The concentration ratio is four to one: 0.1 divided by 0.025 equals four. That is a ratio of labeled concentration, not a fourfold difference in skin exposure or outcome. The distinction is developed in our guide to tretinoin strength and vehicle. The trial challenges a simple assumption that quadrupling concentration necessarily produces proportionately better visible results.
The large percentages describe tissue, not wrinkle reduction
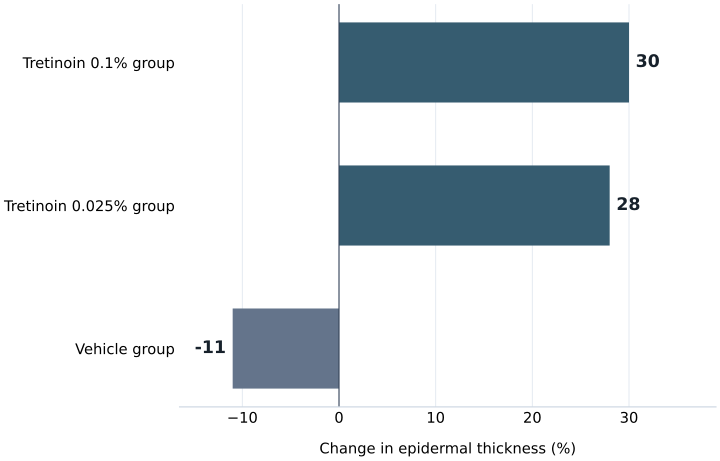
After 48 weeks, epidermal thickness increased by 30% with 0.1% tretinoin and 28% with 0.025%, compared with an 11% decrease with vehicle. The epidermis is the skin’s outer cellular layer. These measurements concern tissue structure; they do not mean that wrinkles improved by 30% or that 30% of participants achieved a cosmetic response.
Vascularity was measured through dermal endothelial cell area, a tissue measure related to the cells lining blood vessels. It increased by 100% and 89% in the active groups, compared with a 9% decrease with vehicle. A 100% increase means that this particular measure doubled relative to its starting value. It does not mean that overall skin health doubled or that every aspect of circulation improved.
As arithmetic interpretation, the reported thickness changes differ from vehicle by 41 and 39 percentage points; the vascularity changes differ by 109 and 98 percentage points. These subtractions summarize separation between reported percentage changes, not adjusted treatment effects with known precision. The abstract supplies no confidence intervals for these comparisons.
Reported 48-week findings: clinical outcomes and tissue measurements answer different questions.
| Measure | Reported result | Appropriate interpretation |
|---|---|---|
| Overall facial photoaging | Both active creams improved versus vehicle; no significant active-arm difference | Observed clinical benefit without formal proof of equivalence |
| Epidermal thickness | 0.1%: +30%; 0.025%: +28%; vehicle: −11% | Change in a tissue measurement, not percent wrinkle reduction |
| Dermal vascularity | 0.1%: +100%; 0.025%: +89%; vehicle: −9% | Change in endothelial cell area, not a cosmetic response rate |
| Redness and scaling | Significantly greater with 0.1% than 0.025% | A tolerability difference without published abstract event rates |
Irritation and improvement did not rise together
The higher concentration produced statistically significantly greater irritant effects, specifically erythema and scaling. Erythema means redness. The abstract reports this difference across several analyses but does not provide the proportion affected, severity distributions, duration, or irritation-related withdrawal counts. It therefore establishes a direction of difference without quantifying an individual’s likelihood of irritation.
The scientific importance is the separation between tolerability and benefit. If greater irritation were the main driver of improvement, substantially more irritation might be expected to accompany more improvement. Instead, the two strengths had similar observed clinical and tissue effects. The authors interpreted that pattern as suggesting that mechanisms other than irritation dominate the response.
That is a mechanistic inference, not a complete causal demonstration. The trial did not separately manipulate irritation while holding every other treatment feature constant. Nor does it prove that improvement always occurs without irritation or that irritation is irrelevant in every setting. It does weaken the idea that visible peeling is a necessary measure of how well tretinoin is working.
Completer counts leave an important uncertainty
The phrase 99 completers matters because it identifies who reached the reported endpoint, not necessarily everyone who began treatment. Without the starting denominator, the abstract cannot establish a completion percentage or attrition rate. It would be incorrect to describe this as a trial that randomized exactly 99 people.
Missing follow-up could affect interpretation if people who stopped differed systematically from those who remained. For example, treatment intolerance could influence completion, but the abstract does not establish that this occurred or whether it differed by group. The available counts cannot resolve how withdrawals were handled in the clinical analyses.
Other unresolved questions include the timing of improvement, variation in response, and whether particular baseline characteristics changed the concentration comparison. The abstract reports no subgroup estimates or confidence intervals to answer these questions. It also does not identify a sponsor or funder. These are specific information gaps, not reasons to disregard the controlled comparison that was reported.
Immune markers were measured, but broad immune claims do not follow
Investigators examined several immune-related features: keratinocyte expression of HLA-DR and intercellular adhesion molecule-1, epidermal Langerhans cells, and epidermal and dermal T lymphocytes. Keratinocytes are the predominant epidermal cells; the other measurements concern immune signaling or immune-cell populations in skin. No significant differences in these markers were found when tretinoin and vehicle treatments were compared.
This result is narrower than saying tretinoin has no immune effects. A nonsignificant comparison may reflect a genuinely small effect, limited measurement sensitivity, or insufficient statistical precision. The abstract does not provide estimates and confidence intervals that would distinguish these possibilities or establish the largest effect compatible with the observations.
Likewise, unchanged immune markers do not demonstrate protection against infection, skin cancer, or other clinical disease. The study assessed selected tissue features over 48 weeks, not those outcomes. Keeping clinical appearance, structural measurements, and immune markers separate prevents one favorable category from being used to imply an unmeasured benefit in another.
A two-year trial adds duration, not a concentration ranking
A separate 2005 randomized, placebo-controlled report studied 204 subjects with moderate to severe facial photodamage. Participants received topical tretinoin emollient cream 0.05% or its emollient vehicle on the entire face once daily for up to two years. Unlike the 1995 comparison, it did not directly test two active concentrations.
The abstract reports significantly greater improvement with tretinoin in fine and coarse wrinkling, mottled hyperpigmentation, lentigines, sallowness, overall photodamage severity, and the investigator’s global response assessment. However, it supplies no numerical endpoint changes or confidence intervals. It cannot support a calculated percentage improvement or a ranking of 0.05% against either concentration in the earlier study.
Histology showed no increase relative to vehicle in keratinocytic or melanocytic atypia, dermal elastosis, or adverse stratum corneum findings. Atypia means abnormal-looking cells; the stratum corneum is the outermost skin layer. Procollagen staining increased at month 12 in analyses at three centers. These findings add tissue evidence, but the abstract does not detail irritation rates. They establish neither cancer prevention nor a survival benefit, and funding is not identified in the abstract.
RENOVA 0.02% has its own formula, indication, and safety record
The official RENOVA label describes a specific 0.02% tretinoin oil-in-water emulsion, not the 0.025% or 0.1% creams from the 1995 trial. Its indication is adjunctive mitigation of fine facial wrinkles in people using comprehensive skin care and sunlight avoidance. The label explicitly does not claim elimination of wrinkles, reversal of photoaging, or repair of sun-damaged skin. Bausch Health US LLC is the listed packager; that does not establish sponsorship of the separate historical trials.
The label describes five controlled trials with 324 evaluable active-treatment patients and 332 vehicle patients over 24 weeks. Two trials adequately demonstrated fine-wrinkle efficacy. Among lightly pigmented participants, moderate improvement was reported in 10% with RENOVA plus the skin-protection program versus 3% with vehicle plus that program—a 7-percentage-point difference for that response category, not the total benefit. A separate study in darker-pigmented participants did not demonstrate benefit over vehicle.
Safety is not captured by concentration alone. Among 339 RENOVA users in the label’s adverse-reaction dataset, almost all reported local reactions. A combined category of severe irritation, temporary interruption, or mild topical corticosteroid use affected 32%; about 4% discontinued because of adverse reactions. The label also contains pregnancy and sunlight-sensitivity warnings. Its limitations beyond 52 weeks remain product-specific; the separate two-year 0.05% trial does not automatically replace them.
These evidence records concern different preparations and cannot be substituted for one another.
| Evidence record | Preparation and setting | What it contributes |
|---|---|---|
| 1995 concentration comparison | 0.1% and 0.025% topical creams; 99 completers; 48 weeks | Direct active-strength comparison with clinical, tissue, and irritation findings |
| 2005 longer trial | 0.05% topical emollient cream; 204 subjects; up to two years | Longer vehicle-controlled clinical and histologic observations |
| RENOVA labeling | Specific 0.02% oil-in-water cream; labeled facial use | Product-specific indication, trial results, warnings, and adverse reactions |
| 2007 retinol trial | 0.4% retinol lotion; arm skin; 36 elderly subjects; 24 weeks | Evidence for a different ingredient, anatomical site, and aging population |
The elderly-arm retinol study answers a different question
The 2007 retinol trial involved 36 elderly subjects, averaging 87 years old, living in two senior facilities. In a randomized, double-blind, paired-arm design, study personnel applied 0.4% retinol lotion or vehicle to opposite arms up to three times weekly for 24 weeks. This was naturally aged arm skin, not a head-to-head facial comparison with tretinoin.
Fine-wrinkle scores changed by −1.64 with retinol, with a 95% confidence interval of −2.06 to −1.22, versus −0.08 with vehicle, with an interval of −0.17 to 0.01. Lower scores represented improvement on a 0–9 severity scale. Subtracting these reported changes gives a 1.56-point separation favoring retinol; this is a score difference, not a percentage reduction or a tretinoin-equivalent effect.
The analysis used last observation carried forward, meaning a participant’s latest available measurement could stand in for a later missing one. Biomarker findings came from very small subgroups: six for glycosaminoglycans and four for procollagen staining. Our close reading of the elderly-arm retinol trial explains why those results neither rank retinol against tretinoin nor demonstrate prevention of injury or ulceration.
From trial cream to preparation record
A preparation record identifies more than the active percentage: ingredient, strength, base, additional actives, container, and dispensing details all help establish what a person actually receives. The 1995 abstract identifies cream concentrations but does not disclose enough formulation detail to match a contemporary preparation. Our guides to comparing tretinoin face creams and compounded dispensing records organize those documentary questions.
The editorial interpretation is that trial evidence and purchasing documentation serve different purposes. A trial estimates outcomes under particular conditions; a prescription label or dispensing record identifies a product and its terms. Neither similar concentration nor a familiar ingredient transfers trial results automatically to a compounded combination, another vehicle, an oral route, or a provider. A combination-cream evidence guide addresses the extra uncertainty introduced by additional actives.
For readers checking service documents, the Agency preparation review and Hers preparation review are places to examine documentary terms, not evidence that either service supplies the trial cream or reproduces its outcomes. The scientific implication remains specific: concentration did not track observed benefit proportionately in this comparison, while irritation differed. The unresolved formulation details matter when applying that result elsewhere.
Questions about the evidence
Did the trial prove that 0.025% tretinoin works exactly as well as 0.1%?
No. It found similar observed clinical improvement and no clinically or statistically significant efficacy difference over 48 weeks. The indexed abstract does not report an equivalence margin or confidence interval for that comparison. The result supports questioning an assumed advantage of higher concentration, not asserting identical effects in every patient or preparation.
Does more peeling indicate a better photoaging response?
Not in this comparison. The 0.1% cream caused more redness and scaling without demonstrating greater clinical improvement. This separates irritation from observed benefit and supports mechanisms beyond irritation. It does not establish that irritation never contributes, nor does it make peeling a validated response marker.
Why are the original enrollment and withdrawal numbers important?
They would show how many people started, how many stopped, and whether discontinuation differed between groups. The abstract reports 99 completers without the starting denominator. Consequently, an attrition percentage cannot be calculated, and the extent to which missing follow-up might influence the comparison remains unresolved.
Do the collagen-related findings mean tretinoin prevents skin cancer?
No. Procollagen staining is a marker associated with collagen synthesis, not a cancer endpoint. Neither the two-year abstract nor the concentration comparison establishes cancer prevention. RENOVA labeling states that safety and effectiveness for preventing or treating skin neoplasms or actinic keratoses have not been established.
Can the study determine the best concentration for a current compounded cream?
No. It compared specific historical study creams, and the abstract does not provide their full formulation records. A current compounded cream may differ in base or additional ingredients. Its exact record is necessary to identify the preparation, but documentation alone cannot demonstrate equivalent delivery, tolerability, or clinical outcomes.
What this evidence supports
The 48-week study offers direct evidence that higher tretinoin concentration can increase irritation without demonstrating greater photoaging improvement. Its strongest contribution is the separation of clinical benefit from redness and scaling, supported by similar tissue changes across the active arms. Its main limits are the completer-only denominator available in the abstract, missing precision estimates, and incomplete formulation detail. Longer-term tretinoin findings and official RENOVA labeling add context, but each belongs to a different evidence record. The most defensible reading preserves those boundaries rather than turning one concentration comparison into a universal product ranking.
Research access and limitations
This analysis uses three indexed original research abstracts and the available full official RENOVA labeling. It does not establish access to all study protocols, supplements, allocation details, or participant-level data. Trial exposures identify study arms and are not individualized treatment instructions.
Sources for this preparation discussion
- Two concentrations of topical tretinoin (retinoic acid) cause similar improvement of photoaging but different degrees of irritation. A double-blind, vehicle-controlled comparison of 0.1% and 0.025% tretinoin creams. ↗Indexed original research abstract · Accessed 2026-10-21
- Long-term efficacy and safety of tretinoin emollient cream 0.05% in the treatment of photodamaged facial skin: a two-year, randomized, placebo-controlled trial. ↗Indexed original research abstract · Accessed 2026-10-21
- RENOVA tretinoin cream 0.02% prescribing information ↗Exact drug label; record updated February 24, 2026; internal November 2025 revision, not stock verification · Accessed 2026-10-21
- Improvement of naturally aged skin with vitamin A (retinol). ↗Indexed original research abstract · Accessed 2026-10-21